Building Healthy Bones Part2

Creating A Bone-Healthy Lifestyle

Author: Dr. Stephen Chaney 
calcium supplementsA major study (Tai et al, British Medical Journal, BMJ/2015; 351:h4183) reported that calcium supplementation in women over 50 resulted in only a very small increase in bone density, which translated into a very small (5-10%) decrease in the risk of bone fractures.

The authors concluded that the standard RDA recommendation of 1,000 – 1,200 mg/day of calcium for adults over 50 is unlikely to prevent osteoporosis or reduce the risk of bone fractures.

In last week’s issue of “Health Tips From the Professor” I discussed the many flaws of the study. In brief:

  • The study was a meta-analysis of 51 published clinical studies. Normally, meta-analyses are very strong, but they have an “Achilles Heel” – something called the Garbage-In, Garbage-Out Simply put, this means that the meta-analysis is only as strong as the individual studies that went into it. The authors included 40 years of clinical studies in their meta-analysis, and most of those studies had an inadequate design by today’s standards.
  • The study also made a number of what I would call apples to oranges comparisons that were of questionable validity.

In this week’s issue of “Health Tips From The Professor”, I would like to explore the other side of the coin. I would like to consider the possibility that the study might be correct and discuss what that might mean for you.

Creating A “Bone Healthy” Lifestyle

Despite the concerns I just mentioned. Let’s assume for a minute that the study might just be correct in spite of its many flaws. Let’s assume that the “one size fits all” RDA recommendation of 1,000 – 1,200 mg/day of calcium if you are over 50 may be flawed advice.

If so, perhaps it’s time to say good riddance! It may finally be time to put away the “magic bullet”, “one size fits all” thinking and start seriously considering holistic approaches.

Now that I have your attention, let’s talk about what you can do to prevent osteoporosis – and the role that supplementation should play. Let’s talk about a “bone healthy” lifestyle.

#1: Let’s start with supplementation: Bone is not built with calcium alone. Bone contains significant amounts of magnesium along with the trace minerals zinc, copper and manganese – and all of these are often present at inadequate levels in the diet. Most of us know by now that vitamin D is essential for bone formation, but recent research has shown that vitamin K is also essential (Kanellakis et al, Calcified Tissue International, 90: 251-262, 2012). An ideal calcium supplement should contain all of those nutrients.

#2: Next comes diet: Many of you probably already know that some foods are acid-forming and other are alkaline-forming in our bodies – and that it is best to keep our bodies on the alkaline side. What most of you probably don’t know is that calcium is alkaline and that our bones serve as a giant buffer system to help keep our bodies alkaline. Every time we eat acid-forming foods a little bit of bone is dissolved so that calcium can be released into the bloodstream to neutralize the acid. (My apologies to any chemists reading this for my gross simplification of a complex biological system).

Consequently, if we want strong bones, we should eat less acid-forming foods and more of alkaline-forming foods. Among acid-forming foods, sodas are the biggest offenders, but meat, eggs, dairy, and grains are all big offenders as well. Alkaline-forming foods include most fruits & vegetables, peas, beans, lentils, seeds and nuts. In simple terms, the typical American diet is designed to dissolve our bones. Calcium from diet or supplementation may be of little use if our diet is destroying our bones as fast as the calcium tries to rebuild them.

vitamin d#3: Test your blood 25-hydroxyvitamin D level: 25-hydroxy vitamin D is the active form of vitamin D in our bloodstream. We need a sufficient (20-50 ng/mL) blood level of 25-hydroxy vitamin D to be able to use calcium efficiently for bone formation. We now know that some people who seem to be getting adequate vitamin D in their diet still have low 25-hydroxy vitamin D levels.

In fact, various studies have shown that somewhere between 20-35% of Americans have insufficient blood levels of 25-hydroxy vitamin D. You should get your blood level tested. If it is low, consult with your health professional on how much vitamin D you need to bring your 25-hydroxy vitamin D into the sufficient range.

#4: Beware of drugs: The list of common medications that dissolve bones is a long one. Some of the worst offenders are anti-inflammatory steroids such as cortisone & prednisone, drugs to treat depression, drugs to treat acid reflux, and excess thyroid hormone.

I’m not suggesting that you avoid prescribed medications that are needed to treat a health condition. I would suggest that you ask your doctor or pharmacist (or research online) whether the drugs you are taking adversely affect bone density. If they do, you may want to ask your doctor about alternative approaches, and you should pay a lot more attention to the other aspects of a “bone healthy” lifestyle.

#5: Exercise is perhaps the most important aspect of a bone healthy lifestyle: Whenever our muscles pull on a bone, it stimulates the bone to get stronger. I’ll put the benefits of exercise in perspective in the next section.

Exercise Is A Critical Part of a “Bone Healthy” Lifestyle

weight lifting exerciseInstead of just quoting more boring studies, I’m going to share a couple of stories that help put the importance of exercise into perspective.

The first is my wife’s story. She ate a very healthy diet with minimal meat and lots of fruits and vegetables for years. She took calcium supplements on a daily basis. She walked 5 miles per day and took yoga classes several days each week. Yet when her doctor recommended a bone density scan in her early sixties she discovered she had low bone density. She was in danger of becoming osteoporotic!

Her doctor prescribed Fosamax. My wife tried it for one day and decided the side effects were worse than the disease. So she started asking holistic health practitioners what she should do. They recommended she find a personal trainer and start pumping iron. That was not an easy solution, but it was the right one. When she went in for her second bone scan 3 months later, her doctor excitedly announced that her bone density had increased by 7%. Her doctor said “We never get results that quickly with Fosamax”. When my wife told her she wasn’t taking Fosamax, her doctor became even more excited. (Most doctors actually do prefer holistic approaches. They just don’t recommend them.)

The moral of this story is that you can be doing everything else right, but if you’re not doing weight bearing exercises – if you’re not pumping iron, everything else you are doing may be for naught. Weight bearing exercise is an absolutely essential part of a “bone healthy” lifestyle!

But can exercise do it alone? Some people seem to think so. That brings up my second story. About 40 years ago one of my colleagues at UNC, who was an expert on calcium metabolism, was doing a bone density study on female athletes at UNC. One of the tennis players was nicknamed “Tab”. Tab was a popular soft drink at that time, and Tab was all she drank – no milk, no water, only Tab.

When my colleague measured the bone density of her playing arm, it was normal for a woman of her age. When he measured the bone density of her non-playing arm, it was that of a 65-year-old woman. The reason is simple. When we exercise a particular bone, our body will add calcium to that bone to make it stronger. If we are not getting enough calcium from our diet, our body simply dissolves the bones elsewhere in our body to get the calcium that it needs.

The moral of this story is that exercise alone is not enough. In terms of bone health, we absolutely need exercise to take advantage of the calcium in our diet, and we absolutely need sufficient calcium in our diet to take advantage of the exercise.

This is the most glaring deficiency of the meta-analysis I described last week. None of those studies included exercise. No wonder the increase in bone density was minimal!

Putting It All Together –  Building Healthy Bones

bone healthy lifestyleIf you seriously want to minimize your risk of osteoporosis, there are a few simple steps you can take (simple, but not easy).

  • Consume a “bone healthy” diet that emphasizes fresh fruits and vegetables, minimizes meats, and eliminates sodas and other acidic beverages. For more details on whether your favorite foods are acid-forming or alkaline-forming, you can find plenty of charts on the internet.
  • Minimize the use of medications that adversely affect bone density. You’ll need to work with your doctor on this one.
  • Get plenty of weight bearing exercise. This is an absolutely essential part of a bone healthy lifestyle. Your local Y can probably give you guidance if you can’t afford a personal trainer. Of course, if you have physical limitations or have a disease, you should consult with your health professional before beginning any exercise program.


  • Get your blood 25-hydroxy vitamin D level tested. If it is low, take enough supplemental vitamin D to get your 25-hydroxy vitamin D level into the sufficient range – optimal is even better. Sufficient blood levels of 25-hydroxy vitamin D are also absolutely essential for you to be able to utilize calcium efficiently.
  • Consider a calcium supplement. Even when you are doing everything else correctly, you still need sufficient calcium in your diet to form strong bones. “I’m not necessarily recommending a “one-size fits all” 1,000 to 1,200 mg/day. Supplementation is always most effective when you actually need it. For example:
    • If you are not including dairy products in your diet (either because they are acid-forming or for other health reasons), it will be difficult for you to get adequate amounts of calcium in your diet. You can get calcium from other food sources such as green leafy vegetables. However, unless you plan your diet very carefully you will probably not get enough.
    • If you are taking medications that decrease bone density, that may increase your need for supplemental calcium. Unfortunately, we don’t yet have guidelines on how much is needed.
    • If you do use a calcium supplement, make sure it is complete. Don’t just settle for calcium and vitamin D. At the very least you will want your supplement to contain magnesium and vitamin K. I personally recommend that it also contain zinc, copper, and manganese.
  • Unfortunately, we don’t really have good guidelines for how much calcium you need. Studies like the one described above are challenging the old RDAs, but we don’t yet have enough studies to know how much calcium we need to build strong bones when we are following a “bone healthy” lifestyle that includes proper diet, sufficient 25-hydroxy vitamin D blood levels and plenty of exercise.

What About Medications For Preventing Bone Loss?
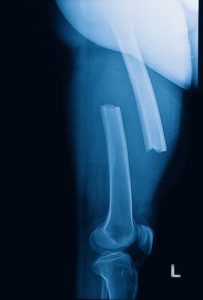
Bone FractureThe danger is that as the conclusions of this meta-analysis get widely publicized and doctors stop prescribing calcium supplements, they probably aren’t going to recommend a holistic approach. They probably won’t recommend a “bone healthy” lifestyle. Instead, they will most likely recommend drugs to prevent bone loss. In fact, the authors of the study described last week specifically praised the use of bisphosphonate drugs (Fosamax and Zometa), and a related drug (Xgeva) that works by a similar mechanism, because they increased bone density by 5-9% over 3 years.

However, these drugs have a dark side, and it’s not just the acid reflux, esophageal damage and esophageal cancer that you hear about in the TV ads. These drugs all act by blocking bone resorption, the ability of the body to break down bone. In the short term, this prevents the bone loss associated with aging and reduces the risk of bone fractures.

However, you might remember from last week’s article that bone resorption is also an essential part of bone remodeling, the process that keeps our bones young and strong. When these drugs are used for more than a few years you end up with bones that are dense, but are also old and brittle. Long term use of these drugs is associated with jaw bones that simply dissolve and bones that easily break during everyday activities. This is yet another example of drugs with side effects that look a lot like the disease you were taking the drug for in the first place.

The Bottom Line

  • A recent study has reported that the RDA recommendation of 1,000 – 1,200 mg/day of calcium for people over 50 provides only a minimal increase in bone density (0.7-1.8%) over the first year or two. This translates into a very small (5-10%) decrease in risk of bone fractures. It did not matter whether the calcium came from dietary sources or from supplementation. The authors concluded that adding extra calcium to the diet, whether from foods or supplements, was not a very efficient way to increase bone density and prevent fractures.
  • This study suffers from some serious flaws, which I discussed in last week’s “Health Tips From the Professor”.
  • Unfortunately, many doctors are likely to take this study to heart. They are likely to stop recommending calcium and other natural approaches and start relying even more heavily on drugs to preserve bone mass. That’s bad news because, while the most frequently proscribed drugs do increase bone mass and prevent fractures short term, they also cause your bones to age more rapidly. After a few years you end up with bones that are dense but are also incredibly brittle and fracture very easily. That’s right. If you use these drugs long enough, they will cause the very condition you were trying to prevent.
  • We should also consider the possibility that this study may just be correct. Let’s assume for a minute that the RDA recommendation of 1,000 – 1,200 mg/day of calcium for everyone over 50 may be flawed advice. If so, it may finally be time to put away the “magic bullet” thinking and start seriously considering holistic approaches to preserving bone mass.
  • A far better choice is to follow a “bone healthy” lifestyle.
    • Start with a “bone healthy” diet. Avoid acid-forming foods like sodas, meats, eggs, dairy, and grains. Instead choose alkaline-forming foods like most fruits & vegetables, peas, beans, lentils, seeds and nuts.
    • Check on the medicines you are using. If they are ones that adversely affect bone density, ask your health professional if there are bone-healthier options.
    • Check your blood level of 25-hydroxy vitamin D on a regular basis. If it is low, consult with your health professional on the amount of vitamin D you need to take to bring your 25-hydroxy vitamin D into the optimal range.
    • Get plenty of weight bearing exercise. This means pumping iron. It is an absolutely essential part of a bone healthy lifestyle. Of course, if you have physical limitations or have a disease, you should consult with your health professional before beginning any exercise program.
  • If you are not getting sufficient calcium from your diet, consider a complete calcium supplement. In addition to calcium and vitamin D, a bone-healthy calcium supplement should at the very least contain magnesium and vitamin K. I also recommend it contains zinc, copper, and manganese.
  • Just don’t rely on a calcium supplement alone to keep your bone density where it should be. If your 25-hydroxy vitamin D isn’t where it should be and/or you aren’t doing weight bearing exercise on a regular basis, your calcium supplement may be almost useless. In my opinion, that may be the biggest take-home lesson from the recent meta-analysis.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

_________________________________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

________________________________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 54 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.
Building Healthy Bones Part1

Do Calcium Supplements Prevent Bone Fractures?

Author: Dr. Stephen Chaney

Building Healthy Bones Part1

Osteoporosis is a debilitating and potentially deadly disease associated with aging. It affects 54 million Americans. It can cause debilitating back pain and bone fractures. 50% of women and 25% of men over 50 will break a bone due to osteoporosis. Hip fractures in the elderly due to osteoporosis are often a death sentence.

For that reason, the RDA for calcium has been set at 1,000 to 1,200 mg/day to reduce the risk of osteoporosis, and calcium supplements are often recommended to reach that target. However, recent headlines are proclaiming that calcium supplements do not actually prevent bone fractures. Are the RDA recommendations wrong? Should you throw out your calcium supplements?

In this article I will review the article behind the study and help you put it into perspective. After all, you don’t really want to know whether calcium supplementation is beneficial for the average adult. You want to know whether it will be beneficial for you.

Bone Metabolism and Osteoporosis 

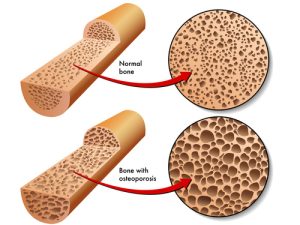
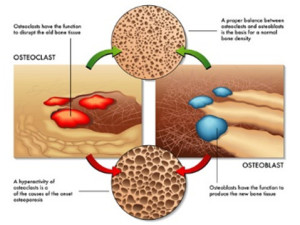
Before you can truly understand osteoporosis and how to prevent it, you need to know a bit about bone metabolism. We tend to think of our bone metabolism osteoporosisbones as solid and unchanging, much like the steel girders in an office building. Nothing could be further from the truth. Our bones are dynamic organs that are constantly changing throughout our lives.

Cells called osteoclasts and osteoblasts constantly break down old bone (a process called resorption) and replace it with new bone (a process called accretion). Without this constant renewal process our bones would quickly become old and brittle (I’ll discuss more about this next week when I talk about the side effects of drugs commonly used to increase bone density).

When we are young the bone building process exceeds bone resorption and our bones grow in size and in density. During most of our adult years, bone resorption and accretion are in balance, so our bone density stays constant. However, as we age bone the bone building process (accretion) slows down and we start to lose bone density. Eventually our bones look like Swiss cheese and break very easily. This is called osteoporosis.

We should also think of our bones as calcium reservoirs.  We need calcium in our bloodstream 24 hours a day for our muscles, brain, and nerves to function properly, but we only get calcium in our diet at discrete intervals. Consequently, when we eat our body tries to store as much calcium as possible in our bones. Between meals, we break down bone material so that we can release the calcium into our bloodstream that our muscle, brain & nerves need to function.

If we lead a “bone healthy” lifestyle, all of this works perfectly. We build strong bones during our growing years, maintain healthy bones during our adult years, and only lose bone density slowly as we age – maybe never experiencing osteoporosis. We always accumulate enough calcium in our bones during meals to provide for the rest of our body between meals.

What is a “bone healthy” lifestyle, you might ask. Because calcium is a major component of bone, the medical and nutrition communities have long focused on calcium as a “magic bullet” that can assure bone health. Once the importance of vitamin D was understood, it was added to the equation.

For years we have been told that if we just get enough calcium and vitamin D in our diets, we would build strong bones when we were young, maintain bone density most of our adult years, and lose bone density as slowly as possible as we age. It is this paradigm that recent studies challenge.

Do Calcium Supplements Prevent Bone Fractures?

Calcium SupplementLet’s start by looking at one of the major studies behind the headlines (Tai et al, British Medical Journal, BMJ/2015; 351:h4183). This was a meta-analysis that included 15 studies (1533 participants) looking at dietary sources of calcium and 51 studies (12,257 participants) looking at calcium supplementation in women.

The results of the meta-analysis were thought provoking, but do not exactly support the headlines you have been reading. For example:

The headlines say, “Calcium Supplements Do Not Prevent Broken Bones”.

  • This study did not actually look at calcium supplementation and the risk of bone fractures. That was a previous study (Boland et al, BMJ 2015, 351:h4580) by the same authors.
  • This study showed that calcium supplementation increased bone density by 0.7-1.8%, which the authors concluded was sufficient to reduce fracture risk by about 5-10%. That’s a disappointingly small effect, but it is not zero – as the headlines suggested.

The headlines say, “It’s better to get your calcium from food than from supplements”.

  • This study showed that it did not matter whether the calcium came from food or from supplements. The increase in bone density was identical.

Garbage-In, Garbage-Out

Garbage In Garbage OutMeta-analyses such as this one can be very strong, but they can also suffer from the “garbage-in, garbage-out” phenomenon. In short, if most of the studies that went into the meta-analysis were poorly designed, the conclusions of the meta-analysis will be unreliable.

The problem is that many of the individual studies were conducted 10, 20, 30 or 40 years ago when our knowledge of bone metabolism was incomplete.

  • Thirty or 40 years ago it was “state of the art” to just use a calcium supplement. Then we learned that adequate vitamin D was essential for efficient calcium utilization.
    • Most of the studies included in this meta-analysis looked at calcium supplementation without vitamin D. Only 13 of the studies (25%) included vitamin D.
  • Ten or 20 years ago it was “state of the art” to just use a calcium supplement with vitamin D. Then we learned that the blood level of 25-hydroxyvitamin D (the active form of vitamin D in the bloodstream) did not necessarily reflect vitamin D intake from the diet. In today’s world a study in which the 25-hydroxy vitamin D level is not measured should be considered sub-standard.
    • Only 18 (35%) of the studies measured baseline 25-hydroxy vitamin D levels.
  • If dietary calcium intake at baseline is already adequate, it is illogical to expect additional calcium to significantly increase bone density.
    • The baseline calcium intake was <800 mg/day (clearly inadequate) in only 26 (51%) of the studies. Baseline calcium intake was either not determined in other studies or was already in the adequate range prior to supplementation.
  • In the future, we will probably want to include exercise as a component in the study (more about that next week). None of the studies included exercise as a component

In short, by today’s standards many, if not most, of the studies included in the meta-analysis had an inadequate design.

If I had designed the meta-analysis, I would have been a lot more restrictive in the studies I included.Skeptic

  • I would have started by including only studies in which the baseline intake of calcium was <800 mg/day. If you want to critically evaluate whether calcium supplementation has a beneficial effect, you need to start with people who have an inadequate dietary intake of calcium. If their diets are already calcium sufficient, supplementation is unlikely to have any benefit.
  • At the very least I would only include studies that used calcium supplements containing 400-800 IU of vitamin D as well. In fact, based on the latest data I would make sure that the calcium supplement I used also contained adequate levels of magnesium, vitamin K, zinc, copper and manganese. All of those have been shown to be important for bone formation, and we cannot assume they are present at sufficient levels in their diet (more about that next week).
  • I would only include studies that measured blood levels of 25-hydroxy vitamin D at baseline and following supplementation with vitamin D so that we knew that the 25-hydroxy vitamin D level was sufficient to support optimal calcium utilization.
  • Finally, I would only include studies that specifically measured the effect of exercise on calcium utilization or included exercise as an integral part of their study.

The number of studies included in the meta-analysis would be much less, but they would all be high quality studies.

Finally, the authors also noted that several studies in the supplement group showed significantly greater (2.5 – 5.0%) increase in bone density. They dismissed them as outliers. I would have preferred a closer look at those studies to see if there was anything about the population group or study design that might explain the greater bone density increase in those studies.

Apples and Oranges

apples orangesBecause the authors included a wide variety of clinical studies, they were able to state that “Increases in bone mineral density were similar in trials of calcium monotherapy [calcium by itself] versus co-administered calcium and vitamin D…and in trials where baseline dietary calcium intake was <800 [clearly insufficient] versus >800 [probably sufficient] mg/day.”

This could be considered a strength of their meta-analysis, but they are only valid comparisons if other important features of the studies being compared were uniform – i.e. they were comparing apples to apples.

But what if they were comparing apples and oranges?

For example, we know that vitamin D is required for efficient calcium utilization. When the authors compared studies having a baseline calcium intake of <800 mg/day with studies having a baseline calcium intake of >800 mg/day, they did not even check to see whether use of vitamin D was evenly distributed between the two groups.

  • If most of the studies with a baseline calcium intake of <800 mg/day did not include vitamin D with their calcium supplements, the authors would be comparing apples and oranges. The comparison would be invalid.

Similarly, we also know that if calcium intake at baseline is adequate, adding more calcium is unlikely to increase bone density significantly. When the authors compared studies with and without vitamin D, they did not even check to see whether baseline calcium intake was evenly distributed between the two groups.

  • If the participants in most of the studies utilizing supplements providing both calcium and vitamin D were already consuming sufficient calcium at baseline, they would be comparing apples to oranges. Again, the comparison would be invalid.

The authors of the meta-analysis simply did not provide the detail needed to determine whether their comparisons were apples to apples or apples to oranges. Thus, what seemed to be a strength of their study is actually a major weakness.

The Bottom Line

  • A recent study has reported that the RDA recommendation of 1,000 – 1,200 mg/day of calcium for people over 50 provides only a minimal increase in bone density (0.7-1.8%) over the first year or two. This translates into a very small (5-10%) decrease in risk of bone fractures.

It did not matter whether the calcium came from dietary sources or from supplementation. The authors concluded that adding extra calcium to the diet, whether from food or supplements, was not a very efficient way to increase bone density and prevent fractures.

  • This study suffers from some serious flaws. It is a meta-analysis of previous clinical trials looking at the effects of calcium on bone density. Meta-analyses can be very strong studies because they average the effects of many individual studies. However, meta-analyses can also suffer from the “garbage-in, garbage-out” phenomenon.

Simply put, the quality of the meta-analysis is only as good as the studies that go into it. In this case the meta-analysis included many clinical studies that were done 10, 20, 30 and even 40 years ago. Based on what we now know about bone metabolism, the design of many of those early studies was clearly inadequate (details are given in the article).

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure or prevent any disease.

__________________________________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_______________________________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.

Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”.

Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry textbooks for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 54 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.
Are Omega-3s Needed For Strong Bones?

Why Are Omega-3s Needed For Strong Bones?

Author: Dr. Stephen Chaney

fish and fish oilOsteoporosis is one of the dreaded diseases associated with aging.

  • Over 50% of women and 25% of men will develop osteoporosis in their lifetime.

And the risk of osteoporosis is highest for Caucasians.

  • Over 40% of white women and 13% of white men will develop an osteoporotic fracture in their lifetime.

And osteoporotic fractures can be deadly. Bone fractures increase the risk of death 3-5-fold within the next few months. Moreover, the quality of life is diminished, and the risk of death is elevated for years after the fracture occurs.

So, if you are like many people, you are doing all you can to keep your bones strong so you will minimize your chances of developing osteoporosis. You probably even have a check list:

  • Resistance exercise (strengthens the bones you pull on)……Check
  • Walking (strengthens hip and leg bones)………………………Check
  • Adequate calcium & vitamin D (essential for strong bones)…Check
  • Magnesium & vitamin K (also important for strong bones)…..Check
  • Adequate protein (Muscle pulling on bone strengthens it)…..Check
  • Adequate omega-3s………………………………………………What!!!

You probably didn’t know about omega-3s. But recent research suggests they may also play a role in building strong bones and preventing osteoporosis. For example, studies show that omega-3s may influence bone metabolism by:

  • Enhancing absorption of calcium from the intestine.
  • Reducing the rate at which bone is broken down.
  • Increasing the rate at which new bone is built.

But large-scale population studies showing that omega-3 intake influences the risk of developing osteoporosis are lacking. The study ( Z Liu et al, Frontiers In Nutrition, 11: 1467559, 2023) I am discussing today was designed to fill that gap.

But before I describe the study, I should give you a quick review of bone metabolism.

Biochemistry 101: Bone Metabolism

bone metabolism osteoporosisTo truly understand osteoporosis and how to prevent it, you need to know a bit about bone metabolism. We tend to think of our bones as solid and unchanging, much like the steel girders supporting an office building. Nothing could be further from the truth. Our bones are dynamic organs that are in constant change throughout our lives.

Cells called osteoclasts constantly break down old bone (a process called resorption), and cells called osteoblasts replace it with new bone (a process called accretion). Without this constant renewal process our bones would quickly become old and brittle.

In short, our bones are not inert. They are in constant flux. If we exercise regularly and get enough calcium, vitamin D, magnesium, and vitamin K from our diet, bone metabolism looks like this as we age.

  • When we are young, osteoblast activity predominates, so accretion (the bone building process) exceeds bone resorption, and our bones grow in size and density.
  • When we are adults, osteoblast and osteoclast activity are in balance. Thus, bone accretion and resorption are in balance, and our bone density stays constant. The top portion of the picture above depicts what happens when osteoclast and osteoblast activity are in balance.
  • However, as we age osteoclast activity predominates, and we start to lose bone density. Eventually our bones look like Swiss cheese and break very easily. This is called osteoporosis. The bottom portion of the picture depicts this.

We should also think of our bones as calcium reservoirs.  We need calcium in our bloodstream 24 hours a day for our muscles, brain, and nerves to function properly, but we only get calcium in our diet at discrete intervals. Consequently:

  • When we eat our body tries to store as much calcium as possible in our bones.
  • Between meals, we break down bone material so that we can release the calcium into our bloodstream that our muscle, brain & nerves need to function.

If we lead a “bone healthy” lifestyle, all of this works perfectly. We build strong bones during our growing years, maintain healthy bones during our adult years, and only lose bone density slowly as we age – maybe never experiencing osteoporosis. We always accumulate enough calcium in our bones during meals to provide for the rest of our body between meals.

I should note that this is the current paradigm for bone metabolism. The study I am discussing today is asking whether omega-3 fatty acids should also be considered as part of a bone-healthy lifestyle.

How Was This Study Done?

clinical studyThe investigators used data from NHANES (National Health And Nutrition Examination Survey), an ongoing study to assess the health and nutritional status of adults and children in the United States. Specifically, this study combined data from participants from the 2005-2010, 2013-2014, and 2017-2018 NHANES surveys.

The participants included in the survey:

  • Were greater than 50 years old.
  • Had completed two 24-hour dietary recall surveys to determine the omega-3 content of their diet (The average omega-3 intake of the two surveys was used for this study).
  • Had a bone mineral density (BMD) test performed using dual-energy X-ray absorptiometry (DXA) scans.

Participants were excluded from the study if they had incomplete diet or bone mineral density data or if they had a disease that affects bone metabolism.

A total of 8,889 participants were included in the study. They were divided into 3 categories based on their bone density:

  • Normal bone density (4,421 participants)
  • Osteopenia (3,952 participants)
  • Osteoporosis (516 participants)

Finally, the participants were divided into quartiles based on their omega-3 intake, and omega-3 intake was correlated with bone density.

Are Omega-3s Needed For Strong Bones?

Healthy BoneThe study results were as follows:

  • Omega-3 intake was inversely related to bone density. Simply put, that means:
    • The highest intake of omega-3s was observed in the group with normal bone density, and…
    • The lowest omega-3 intake was observed in the osteoporosis group.

When the participants were divided into quartiles based on their omega-3 intake:

  • Participants with the highest omega-3 intake were 29% less likely to develop osteoporosis than participants with the lowest omega-3 intake.

When the investigators looked at subgroups, they found stronger effects of omega-3s on osteoporosis risk for women, people under 60, and non-smokers. Specifically:

  • Women with the highest omega-3 intake were 35% less likely to develop osteoporosis.
  • People under 60 were 49% less likely to develop osteoporosis.
  • Non-smokers were 36% less likely to develop osteoporosis.

The investigators concluded, “This study demonstrates a significant inverse relationship between dietary omega-3 fatty acid intake and osteoporosis risk, suggesting omega-3s play a crucial role in bone health. However, further longitudinal studies are needed to confirm these studies and refine dietary recommendations for osteoporosis prevention.”

Why Are Omega-3s Needed For Strong Bones?

QuestionsYou are probably thinking,

  • “Calcium and magnesium are part of bone structure. Vitamin D and vitamin K facilitate the incorporation of calcium into bone. So, it is logical that these nutrients would be important for strong bones.”
  • “But what role do omega-3s play? They aren’t incorporated into bone, and they don’t affect calcium metabolism.”

Here is what the authors said about that:

  • Omega-3s are anti-inflammatory. They decrease production of the pro-inflammatory cytokines that stimulate osteoclasts – the cells that break down bone.
  • EPA and DHA are also converted to prostaglandins that stimulate osteoblasts – the cells that build new bone.
  • Finally, the authors said, “Omega-3 fatty acids, especially EPA and DHA, have been shown to enhance calcium absorption in the gut – a process crucial for maintaining optimal bone mineral density…Omega-3s …do this by altering the lipid composition of cell membranes, thereby affecting calcium channels and enhancing calcium availability for bone tissue.”

Let me help you understand that statement.

  • While we might think of our cell membranes as rigid structures, they are quite fluid. The closest analogy I can think of is a large lake. You may not see any waves or ripples, but if a leaf drops on the surface it doesn’t stay in one place. It moves. We can think of calcium channels in our membrane like leaves on the water. They move across the cell membrane.
  • How fast they move depends on the fluidity of the cell membrane. This is determined by the lipids (fats) in the cell membrane, which in turn is determined by the fats in our diet. This is the one case where it is literally true that we are what we eat.
    • When we have lots of saturated fats in our cell membranes, fluidity is low, and calcium channels move slowly across the membrane.
    • When we have omega-3 fats in our cell membrane, fluidity is high, and calcium channels move quickly across the cell membrane.
  • Calcium channels work best when they cluster together, and this works best with highly fluid, omega-3-rich cell membranes.

What Does This Mean For You?

Question MarkThis study strongly suggests that omega-3s play a role in bone health, and they may be important for reducing our risk of osteoporosis. The authors concluded, “The findings suggest that omega-3 fatty acids play a critical role in bone health, supporting the need for dietary recommendations that encourage omega-3 consumption as a preventative measure against osteoporosis.”

However, this is the first study of its kind, which is why the authors said, “Further longitudinal studies are needed to confirm these findings.”

However, my biggest concern with the study is that it did not include information on the intake of the other nutrients essential for bone health (calcium, vitamin D, magnesium, and vitamin K). We don’t know at present the importance of omega-3s for preventing osteoporosis relative to dietary intake of other bone-healthy nutrients. For example:

  • Are omega-3s important for bone health when intake of calcium and/or the other bone-healthy nutrients are low?
  • Or are omega-3s equally important for bone health under all conditions?

However, the good news is that omega-3s have many proven health benefits such as heart health, controlling blood pressure, and reducing inflammation. If they are also important for bone health, we can consider it an unexpected benefit.

With that in mind, there are two important takeaways for you:

  • Omega-3s were most effective at preventing osteoporosis in people under 60. That is entirely consistent with what we know about preventing osteoporosis. The best prevention strategy is to build strong bones while you are young and maintain strong bones as long as possible in your adult years.
  • The optimal reduction of osteoporosis risk in this study was seen with an omega-3 intake of 1.86 g/d. While more studies are needed to define the optimal dose of omega-3s for reducing osteoporosis risk, this dose is within the “sweet spot” for the other omega-3 benefits I mentioned.

The Bottom Line 

A recent study asked whether omega-3 fatty acids reduce the risk of osteoporosis.

The study found:

  • Omega-3 intake was inversely related to bone density.
  • When the participants were divided into quartiles based on their omega-3 intake:
  • Participants with the highest omega-3 intake were 29% less likely to develop osteoporosis than participants with the lowest omega-3 intake.
  • When the investigators looked at subgroups, they found stronger effects of omega-3s on osteoporosis risk for women, people under 60, and non-smokers.

The investigators concluded, “This study demonstrates a significant inverse relationship between dietary omega-3 fatty acid intake and osteoporosis risk, suggesting omega-3s play a crucial role in bone health. This supports the need for dietary recommendations that encourage omega-3 consumption as a preventative measure against osteoporosis.”

For more information on this study, why omega-3s reduce osteoporosis risk, and what this study means for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 _____________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading Biochemistry textbooks for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 53 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

 

Is Folate Needed For Strong Bones?

Why Is Folate Needed For Strong Bones?

Author: Dr. Stephen Chaney

calcium supplementsWhen most people think of the nutrients required to build strong bones, they just think of calcium and vitamin D. This is understandable because these two nutrients are essential for building healthy bone.

But in reality “it takes a village” to build strong bones.

  • The bone matrix also contains magnesium, zinc, copper, and manganese. They are also needed.
    • Fun fact: As an undergraduate at the University of Southern California my wife, Suzanne, worked for Dr. Paul Saltman, the biochemist who discovered the importance of these nutrients for building healthy bone.
  • Vitamin C is required to build collagen, the foundation on which bone is built, and the cartilage that helps bones resist fractures.
  • Vitamin K delivers calcium to osteoblasts, the cells responsible for building bone.

But a new study (L Zhou et al, BMC Musculoskeletal Disorders, 25: 487, pages 1-9, 2024) suggests that folate is also important for building strong bones and preventing osteoporosis as we age. I didn’t see that one coming. So, let me start by explaining why folate may be important for bone health before I review the study.

Why Is Folate Needed For Strong Bones?

Question MarkThere are four facts we need to know about human metabolism to understand the effect of folate on bone health.

Fact 1: We tend to think of bone as a permanent, unchanging part of our body. But that’s not true. As we move about our bones experience wear and tear. As they age they become more brittle and susceptible to fracturing.

So, our bodies have a process for continuously removing old bone and replacing it with new bone. Although you don’t notice the change, your bones today are not the same bones you had 10 or 15 years ago. They are continually being renewed.

The cells responsible for removing the old bone are called osteoclasts, and the cells responsible for building new bone are called osteoblasts. It is the perfect balance between osteoclast and osteoblast activity that keeps our bones strong.

Fact 2: When cellular folate levels are low, an amino acid metabolite called homocysteine accumulates in our cells and in our blood.

Fact 3: (This is the one I didn’t know until I looked it up): Homocysteine increases osteoclast activity and decreases osteoblast activity.

This tips the balance towards breaking down our bones. For young people that makes it more difficult to build strong, healthy bones. For older people that increases the risk of osteoporosis.

Fact 4: To clear up any confusion before we get started, I should tell you that the term “dietary folates” often includes folates from foods and folic acid from supplements. That is because folic acid is efficiently taken up by our cells and converted to folates in the cell.

And when methyl folate and folic acid are compared head to head in clinical studies, methyl folate offers no advantage over folic acid, even in individuals with mutations in the MTHFR gene. For more detail on this statement, go to https://www.chaneyhealth.com/healthtips/ and type “methy folate” in the search box.

How Was The Study Done?

Clinical StudyThe investigators used data from the CDC’s 2017-2020 NHANES (National Health And Nutrition Examination Survey) database. The NHANES program has been obtaining health and nutrition data from approximately 5,000 US citizens a year since 1969. Every 4 years the data are compiled into a database that can be used for studies like this one.

The investigators excluded participants who were missing important information such as calcium, vitamin D, or folate intake and bone density measurements. This left 2297 participants for the current study.

The participants were 49.9% female, 73% white, and the average age was 64 years. The prevalence of osteoporosis in this group was 6.92%, which is similar to other estimates of osteoporosis prevalence in this age group.

Dietary intake was based on two 24-hour dietary recalls. Bone density in the femur region was assessed by DXA radiological imaging. Osteoporosis was defined as a bone mineral density of <0.64 g/cm2 for women and <0.68 g/cm2 for men.

The study measured the correlation between dietary folate intake and prevalence of osteoporosis.

Is Folate Needed For Strong Bones?

folic acidThe investigators separated the participants into 3 groups based on dietary folate intake: lowest (<264 mcg/day), middle (264-390 mcg/day), and highest (>390 mcg/day). For reference the daily value (DV) for folate is 400 mcg/day for adults in this age group.

When adjusted for other factors that affect bone density such as calcium, vitamin D, smoking, and alcohol consumption, those with the highest dietary intake of folates compared to those with the lowest dietary intake of folates:

  • Decreased their risk of osteoporosis by 70%.

And when the data were broken down by gender and age, the highest intake of dietary folates:

  • Decreased the risk of osteoporosis by 82% for women.
    • Also, decreased the risk of osteoporosis for men. But the decrease was not statistically significant (Because men are less likely to develop osteoporosis than women, a much larger study would likely be required to show a statistically significant decreased risk for men.)
  • Decreased the risk of osteoporosis by 70% for people over 60.
    • Did not significantly decrease the risk of osteoporosis for people under 60 (Osteoporosis is rare in people under 60.)
  • In short, adequate intake of folates (including folic acid) significantly decreases the risk of osteoporosis for those who are at highest risk, namely postmenopausal women over 60.

When the investigators did a dose response plot they found an L-shaped relationship between dietary folate and the risk of osteoporosis. They concluded that:

  • Dietary folate intake between 264 and 569 mcg/day was effective in preventing osteoporosis in post-menopausal women. Intakes above 569 mcg/day provided little or no additional benefit.

The authors concluded, “This finding suggests the potential importance of dietary folate for preventing and managing osteoporosis.”

“However, further longitudinal research and randomized controlled trials are necessary to elucidate the causal association between dietary folate intake and the risk of osteoporosis.”

What Does This Study Mean For You?

Healthy BoneI am not suggesting that you should throw out your calcium and vitamin D supplement and rely on a folic acid supplement to build strong bones and prevent osteoporosis.

Calcium and vitamin D are absolutely essential for building strong bones. But they are not sufficient by themselves. It takes a holistic approach to build strong bones.

I have previously alerted you to the importance of vitamin C, vitamin K, magnesium, zinc, copper, and manganese for building strong bones. This study suggests I may need to add folic acid to the list. And who knows how many additional nutrients may play a role we don’t yet know about.

And it’s not just nutrients. There are many other lifestyle factors that influence the health of our bones. I have described what it takes to have a “bone healthy lifestyle” in a previous issue of “Health Tips From the Professor”.

This is why so many studies looking at the effect of calcium/vitamin D supplements on the risk of developing osteoporosis have come up empty. These studies were asking if calcium and vitamin D were “magic bullets” that could prevent osteoporosis on their own.

The answer to that question appears to be, “No”. But it isn’t the right question. As I have said before, “When clinical studies ask the wrong question, they get the wrong answer.”

Calcium and vitamin D are essential for bone formation, but they aren’t sufficient by themselves. It takes a village. Any study that ignores that is doomed to failure.

What does that mean for you? My recommendation is simple. If you want to build strong bones and reduce your risk of osteoporosis:

  • Start with a comprehensive multivitamin/multimineral supplement to make sure your bases are covered.
  • If your intake of calcium and vitamin D are below DV values (1,300 mg of calcium and 600-800 IU of vitamin D for adults in this age range), consider a calcium/vitamin D supplement.

The Bottom Line

A recent study suggests that dietary folate is important for building strong bones and preventing osteoporosis in post-menopausal women.

In this article I review the study, put it into perspective, and discuss what it means for you.

For more details about this study and what it means for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 ______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance 

____________________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are Calcium Supplements Safe?

What Does This Study Mean For You?

Author: Dr. Stephen Chaney 

Pendulum
Pendulum

Should you avoid calcium supplements because they increase your risk of heart disease? Some headlines and blog posts would have you believe that. You may have been told that by your doctor. But is it true?

Unfortunately, this is another example of the swinging pendulum that we often see in supplement studies. One day a study comes out saying that calcium supplements increase the risk of heart disease. A few months later another study comes out saying that is not true. Calcium supplements don’t increase heart disease risk.

The pendulum keeps swinging until you are totally confused. You don’t know what to believe. And “experts” (including your doctor) pick one side or the other depending on what they believe about supplements in general.

I have told you before that good scientists wait until multiple studies have been done and base their opinion based on what the preponderance of studies show. I can tell you that multiple studies have been done and the preponderance of studies show that calcium supplements do not increase the risk of heart disease. But that doesn’t prove that calcium supplements are safe. It just shows they are likely to be safe.

That is why the authors of the current study (X Huo et al, Current Developments In Nutrition, volume 7, Issue 3: 100046, March 2023) analyzed the weaknesses of previous studies and tried to design a study that lacked those weaknesses.

How Was This Study Done?

clinical studyThe investigators searched through the literature to identify all placebo-controlled, randomized clinical trials (the gold standard for clinical studies) assessing the effects of calcium supplements alone or calcium supplements with vitamin D on heart disease, stroke, and all-cause mortality.

They restricted their analysis to studies with at least 500 participants that lasted for at least a year. They further restricted their analysis to studies whose authors were willing to share unpublished data on the number of participants in each treatment group who had a heart attack, stroke, or any other kind of heart disease; died from heart disease; or died from all causes during the study.

They ended up with 11 clinical studies in their analysis. The breakdown was as follows:

  • Seven studies with 8,634 participants compared calcium alone with placebo.
    • Participants in these studies averaged 71 years old and were 79% female.
    • The daily calcium dose varied from 1.0 to 1.5 g/day.
    • The mean duration of treatment was 4.1 years (range = 2-5 years).
  • Six studies with 46,804 participants compared calcium plus vitamin D with placebo.
    • Participants in these studies averaged 65 years old and were 98% female.
    • The daily calcium dose varied from 1.0 to 1.5 g/day and the daily vitamin D dose ranged from 400 to 2,000 IU/d.
    • The mean duration of treatment was 6 years (range = 1.5-7 years).
  • In case you were wondering about the math, some studies included both calcium alone versus placebo and calcium plus vitamin D versus placebo.

The authors then combined the data from all 11 studies and performed a meta-analysis on the effect of calcium alone on adverse heart outcomes and calcium plus vitamin D on adverse heart outcomes.

Are Calcium Supplements Safe? 

calcium supplementsThe results were clear-cut.

  • Calcium alone was not significantly associated with any increased risk of heart attack, stroke, heart disease of any kind, deaths from heart disease, and deaths from all causes.
  • Calcium with vitamin D was not significantly associated with any excess risk of heart attack, stroke, heart disease, deaths from heart disease, and deaths from all causes.

In their discussion, the authors pointed out two caveats to their conclusions:

  • In the calcium only portion of the meta-analysis the number of participants who experienced a stroke or types of heart disease other than heart attack and stroke was very small. So, they could not exclude an absolute increased risk of 0.3-0.5% per year for these types of rare events.
  • The participants in the 11 studies included in their meta-analysis were not selected based on their risk of heart disease. So, the authors could not exclude the possibility that calcium supplements might increase the risk of heart disease in people who were already at high risk of heart disease.

The authors concluded, “This meta-analysis demonstrated that calcium supplements were not associated with any significant hazard for heart disease, stroke, or all-cause mortality…Hence, for people with low bone density and low absolute risks of heart disease, the present report demonstrates no concern about excess heart disease risks associated with calcium supplements.

However, further large trials are needed to assess the efficacy and safety of combined supplementation with calcium and vitamin D for the prevention of osteoporotic fracture in older people at high risk of heart disease.”

What Does This Study Mean For You?

Questioning WomanAs I said above, the preponderance of evidence suggests that calcium supplementation does not increase your risk of heart disease. This study reinforces that conclusion.

I can’t guarantee that some future study won’t come to the opposite conclusion, and the pendulum will swing again. And I can’t guarantee that your doctor has kept up with the most recent literature on calcium supplementation and heart disease risk.

The authors of this study also pointed out that we don’t have any clinical studies on the effect of calcium on heart disease risk if you are already at high risk of heart disease. So, if you are at high risk of heart disease, any advice that I or your doctor give you about calcium supplementation might be wrong. We simply don’t know.

Finally, I realize that you may be equally confused about whether calcium supplementation can strengthen your bones and reduce your risk of osteoporosis. I won’t discuss that question today. Instead, I will refer you to two previous articles I have written in “Health Tips From the Professor” on that topic.

The first article discusses the flaws in previous studies claiming that calcium supplements are ineffective at increasing bone density and preventing osteoporotic fracture.

The second article describes a bone-healthy lifestyle.

The Bottom Line

While the preponderance of studies have shown that calcium supplementation does not increase the risk of heart disease, that conclusion remains controversial.

To clarify that issue, a group of investigators searched through the literature to identify all placebo-controlled, randomized clinical trials (the gold standard for clinical studies) assessing the effects of calcium supplements alone or calcium supplements with vitamin D on heart disease, stroke, and all-cause mortality. They then performed a meta-analysis of those clinical studies.

Their meta-analysis showed that:

  • Calcium alone was not significantly associated with any increased risk of heart attack, stroke, heart disease of any kind, deaths from heart disease, and deaths from all causes.
  • Calcium with vitamin D was not significantly associated with any excess risk of heart attack, stroke, heart disease, deaths from heart disease, and deaths from all causes.

This study strengthens the conclusion that calcium supplementation does not increase the risk of heart disease.

For more details about the study and references discussing the effect of calcium supplementation on bone density, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_______________________________________________________________________

About The Author

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

What Nutrients Are Missing In Prenatal Supplements?

Do These Deficiencies Matter?

Author: Dr. Stephen Chaney

healthy pregnancyIf you are a pregnant mom, nothing is more important than the health of your baby. And if you are pregnant or thinking of becoming pregnant, your doctor has probably recommended a prenatal supplement. But does the prenatal supplement he or she recommended provide you with all the nutrients you need?

In a previous issue of “Health Tips From the Professor” I shared two studies that suggested the answer is, “No”. Those studies concluded that most prenatal supplements had little or no vitamin K, choline, DHA, and iodine – all of which are essential for the health of your newborn baby. And while most prenatal supplements contained calcium, the amount they provided was far below recommended levels.

The authors of the first study also made the point that most women going on a prenatal supplement will probably discontinue taking their multivitamin supplement, so a good prenatal supplement should provide all the essential nutrients.

But they don’t. Folic acid, iron, calcium, and vitamin D have long been recognized as essential for a healthy pregnancy. So, virtually every prenatal supplement contained these four nutrients, although calcium is often present in suboptimal amounts. Beyond those four nutrients, the design of prenatal supplements is haphazard. Some contain vitamin K, choline, iodine, or DHA (often in suboptimal amounts). But almost none contain all four nutrients.

And when you consider the other essential nutrients you find in most multivitamins, prenatal supplements often come up empty. Is that a problem? That’s what this study (KM Godfrey et al, PLOS Medicine, 1-27, December 5, 2023) was designed to find out.

How Was This Study Done?

clinical studyThis was a double-blind, placebo-controlled clinical trial, the gold standard for clinical studies. The investigators recruited 1,729 women who were planning to get pregnant from England, Singapore, and New Zealand between 2015 and 2017.

The women were randomly split into two groups:

  • The control group received a supplement containing nutrients that were most frequently included in prenatal supplements in those countries (folic acid, iron, calcium, iodine, and beta-carotene).
  • The intervention group received a supplement containing those nutrients plus riboflavin, vitamin B6, vitamin B12, vitamin D, zinc, inositol, and probiotics).
  • Riboflavin, vitamin B6, vitamin B12, vitamin D, and zinc were included because they are included in most multivitamins but are often missing in prenatal supplements.
  • Inositol was included because some studies have suggested that inositol may reduce the risk of maternal hyperglycemia and gestational diabetes.

Blood samples to assess nutritional status were obtained from all women in the study before the trial started (baseline) and after 1 month of supplementation with either the control or intervention formulation.

Of the women entering the study, 512 went on to have a singleton (one child) pregnancy. For these women supplementation was continued until childbirth. Additional blood samples were obtained in early and late pregnancy and at 6 months postdelivery. [Note: no supplementation was provided to either group postdelivery. And this is also a period of time when most women would be breastfeeding.]

The blood samples were tested for:

  • Blood levels of folic acid, riboflavin, vitamin B6, vitamin B12, and vitamin D.
  • Functional biomarkers of deficiencies of each of these vitamins.

What Nutrients Are Missing In Prenatal Supplements?

Question MarkThere was no difference in maternal hyperglycemia or gestational diabetes between the control group and the intervention group supplemented with inositol, so I will focus on the other nutrients present in the intervention group.

At baseline when subjects were first entered into the study.

  • 29.2% of the subjects had low or marginal status for folic acid.
  • 82.0% of the subjects had low or marginal status for riboflavin.
  • 1.3% of the subjects had low or marginal status for vitamin B6.
  • 9.1% of the subjects had low or marginal status for vitamin B12.
  • 48.7% of the subjects had low or marginal status for vitamin D.
  • 91.0% of the subjects had low or marginal status for one or more of these vitamins.

In the control group receiving folic acid but no riboflavin, vitaminB6, vitamin B12, and vitamin D:

  • Folic acid deficiency fell to 4.1% after 1 month of supplementation (the supplement used by the control group contained folic acid), 1% in early pregnancy, 6.1% in late pregnancy, and rose to 31.8% 6 months after supplementation was discontinued. The intervention group got the same amount of folic acid, and their results were similar.
  • Riboflavin deficiency ranged from 82-92% during pregnancy and returned to 82% 6 months postdelivery.
  • Vitamin B6 deficiency increased to 54% in late pregnancy and returned to 1.2% 6 months postdelivery.
  • Vitamin B12 deficiency increased to 55% in late pregnancy and returned to 12.4% 6 months postdelivery.
  • Vitamin D deficiency ranged from 35-43% during pregnancy and returned to 31% 6 months postdelivery.
  • Functional markers of vitamin B6 deficiency were evident by late pregnancy.

In short, data from the control group fell into 3 categories:

  • The data with folic acid confirm previous studies showing that folic acid in the amount present in most prenatal supplements is effective at preventing folic acid deficiency before and during pregnancy. It also strengthens the argument for continuing folic acid supplementation during breastfeeding.
  • Deficiencies of riboflavin and vitamin D are prevalent in women of childbearing age, but pregnancy does not appear to significantly impact the percentage of women who are deficient in these nutrients.
  • Deficiencies of vitamins B6 and B12 are rare in women of childbearing age, but pregnancy significantly depletes both nutrients.
    • This was particularly evident for vitamin B6. Blood levels of vitamin B6 markers decreased to a level that could impact the functioning of vitamin B6-depended metabolic pathways.

pregnant women taking vitaminsFor the intervention group receiving additional riboflavin, vitamin B6, vitamin B12, and vitamin D:

  • Deficiencies of these vitamins were eliminated by one month of supplementation.
  • Vitamin levels remained adequate during pregnancy.
  • Except for vitamin B12, deficiencies of these vitamins reappeared when supplementation was discontinued for 6 months. The maintenance of adequate B12 levels 6 months after supplementation stopped was expected because the body holds on to its B12 stores very tightly.

In short deficiencies of these nutrients before and during pregnancy could be eliminated by supplementation with levels of these nutrients found in many multivitamins.

The authors concluded, “Over 90% of the trial participants had low concentrations of one or more of folate, riboflavin, vitamin B12, or vitamin D during preconception, and many developed markers of vitamin B6 deficiency in late pregnancy. Preconception/pregnancy supplementation in amounts available in over-the-counter supplements substantially reduces the prevalence of vitamin deficiency and depletion markers before and during pregnancy, with higher maternal plasma vitamin B12 maintained during the recommended lactation period.”

Do These Deficiencies Matter?

New ParentsIt is well established that deficiencies of folic acid and vitamin D cause health risks for the mother and developmental risks for the fetus, so I won’t discuss these nutrients here.

However, the effect of riboflavin, vitamin B6, and vitamin B12 deficiencies on pregnancy is less well known, which is probably why these nutrients are often not added to prenatal supplements.

The authors of the study said small studies have suggested that:

  • Low or deficient riboflavin status may be associated with a higher risk of anemia during pregnancy.
  • Low vitamin B6 status may be associated with an increased risk of preterm birth and development of metabolic health risks in the child.
  • Low vitamin B12 status may be associated with increased risk of gestational diabetes and pre-eclampsia in the mother, and increased risk of neural tube defects, preterm birth, low birth weight, and neurocognitive delays in the baby – with the strongest evidence being an effect on neurocognitive development.

While none of these risks have been definitively proven, the authors point out that deficiencies of these nutrients can easily be eliminated with inexpensive, over-the-counter multivitamin supplements.

What Does This Study Mean For You?

Questioning WomanPerhaps I should start this section by asking why these deficiencies are so common in women of child-bearing age.

The authors speculate that part of the reason is that many women are giving up meat (B12 and iron) and dairy (calcium and riboflavin) for health or environmental reasons.

However, they also point out that a more likely cause is that more than 60% of calories consumed in countries like England, New Zealand, and the United States comes from ultra-processed foods – otherwise known as “empty calories”.

Whatever the cause, the authors conclude, “…the findings suggest a need to reappraise dietary recommendations for preconception and pregnancy to consider further the role of multiple micronutrient supplements for women living in higher-income countries.” I agree.

In a previous “Health Tips From the Professor” article, I reported a recent study showing that most prenatal supplements have either no or inadequate amounts of vitamin K, choline, DHA, iodine, and calcium, nutrients that are absolutely essential for a healthy pregnancy. And I gave recommendations for choosing the best prenatal supplement for you and your child.

That study also noted that many women discontinue their multivitamin supplement when they start taking a prenatal supplement. The current study indicates that practice may be unwise. It shows that:

  • Many women of childbearing age are deficient in one or more of these essential nutrients, and…
  • Essential nutrients not found in most prenatal supplements may also be important for a healthy pregnancy.

So, if you are pregnant or thinking of becoming pregnant, follow this article’s recommendation to start with a well-designed prenatal supplement that provides adequate amounts of folate, iron, calcium, vitamin D, vitamin K, choline, DHA, and iodine and add a multivitamin supplement that provides the other essential nutrients. Alternatively, a simpler approach would be to choose a well-designed prenatal supplement that includes all the essential nutrients. That would be my recommendation.

I would also note this study showed that deficiencies of most of these nutrients reappeared as soon as supplementation was discontinued. Although the authors of this study did not mention it, this reinforces the importance of continuing supplementation during breastfeeding.

The Bottom Line

I have previously reported on a study that concluded many prenatal supplements lack one or more nutrients shown to be important for a healthy pregnancy. But let’s say you have found a prenatal supplement that provides all those nutrients. Is that enough?

Studies show that most women stop taking their multivitamin supplement when they start on a prenatal supplement. But is that a good idea? Are there essential nutrients found in multivitamins, but not in many prenatal supplements that are also important for a healthy pregnancy?

A recent study asked that question in women who were trying to become pregnant. The study found that:

  • Many women of childbearing age are deficient in one or more essential nutrients found in multivitamin supplements but often missing in prenatal supplements, and…
  • Essential nutrients not found in most prenatal supplements may also be important for a healthy pregnancy.

For more details about this study and what it means for you read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 ______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 ______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are Calcium Supplements Heart Healthy?

Should You Follow Your Doctor’s Advice About Calcium Supplementation?

Author: Dr. Stephen Chaney

Heart ConfusionAre calcium supplements good for your heart or bad for your heart? If you don’t know the answer to that question, don’t feel badly. You have every right to be confused. Some studies say that calcium supplements increase heart disease risk while others say they decrease heart disease risk. The headlines have veered between “killer calcium” and “beneficial calcium”.

The trend appears to be moving in a positive direction. In recent years most of the studies have suggested that calcium supplements either decrease heart disease risk or have no effect on heart disease risk.

However, the medical profession has been slow to take note of this trend. Most medical societies and health professionals have focused on earlier studies and are still recommending that their patients get calcium from food rather than from supplements. I will talk more about that recommendation below.

With this context in mind, this week I will review and discuss the results from the latest study (MG Sim et al, Heart, Lung and Circulation, 32: 1230-1239, 2023) on the effect of calcium supplementation on heart disease risk.

How Was This Study Done?

Clinical StudyThe authors of this study performed a meta-analysis of 12 double-blinded randomized clinical trials with 87,899 participants comparing the effect of a calcium supplement versus a placebo on heart disease outcomes (heart attack, stroke, heart failure, cardiovascular mortality, and all-cause mortality).

The studies included in this analysis:

  • Used calcium doses from 500 mg/day to 2,000 mg/day.
  • Used supplements with calcium coming from a variety of sources (calcium carbonate, calcium citrate, calcium gluconolactate, and tricalcium phosphate).
  • Ranged from 18 months to almost 12 years in length.
  • Were performed with population groups from a wide range of countries (United States, England, France, Australia, New Zealand, European Union, Denmark, and Thailand).
  • Included calcium supplements with and without vitamin D.
  • Were primarily (86% of participants) conducted with post-menopausal women. One small study (0.3% of participants) was conducted with non-osteoporotic men. The rest were conducted with mixed populations (men and women) diagnosed with colorectal adenoma.

Are Calcium Supplements Heart Healthy?

calcium supplementsThis is the largest meta-analysis performed to date of double-blind, placebo-controlled randomized clinical trials on the effect of calcium supplementation versus a placebo on heart disease outcomes. This study found no effect of calcium supplementation on:

  • Heart attack.
  • Stroke
  • Heart failure.
  • Cardiovascular mortality.
  • All-cause mortality.

This study also evaluated potential confounding variables and found no effect of calcium supplementation on heart disease risk for:

  • Calcium supplements with and without vitamin D.
  • Dosage of calcium in the supplements (The dosage ranged from 500 mg/day to 2,000 mg/day).
  • Females (I suspect the number of males in this study was too small to come to a statistically significant conclusion).
  • Duration of calcium supplementation ≤ 5 years (The shortest duration of calcium supplementation in these studies was 18 months).
  • Different geographical regions.

However, this meta-analysis reported considerable variation between studies included in the analysis. Simply put,

  • Some studies showed an increase in heart disease risk.
  • Some studies showed a decrease in heart disease risk.
  • Some studies showed no effect on heart disease risk.

What this analysis showed was that when you combine all the studies, the aggregated data is consistent with calcium supplementation having no effect on heart disease risk.

The authors concluded, “Calcium supplementation was not associated with myocardial infraction [heart attack], stroke, heart failure, and cardiovascular/all-cause mortality. Further studies are required to examine and understand these associations.

Should You Follow Your Doctor’s Advice About Calcium Supplementation?

Doctor With PatientAs I said above, most medical societies and health professionals have focused on earlier studies and are still recommending that their patients get calcium from food rather than from supplements. That may be the advice you are getting from your doctor.

Before you assume your doctor isn’t keeping up with the latest science and ignore his or her advice, we should ask why they are giving that advice. The top three reasons most medical societies give for recommending dietary sources of calcium are:

1) Some studies do show an increased risk of heart disease associated with calcium supplementation. The prime directive for health professionals is to do no harm. Yes, the average of all studies shows no effect of calcium supplementation on heart disease risk. But what if the studies showing increased risk are true for some of their patients? Those patients could be harmed. 

Are you someone who might be at increased risk for heart disease if you take calcium supplements. The short answer is we don’t know because previous studies have not asked the right questions. 

In my opinion, it is time to pause additional studies and meta-analyses on calcium supplementation and heart health until we have gone over existing studies with a fine-tooth comb to figure out why the results differ so wildly. For example, we need to ask whether the effect of calcium supplements on heart disease risk is influenced by things like:

    • Age or ethnicity of participants.
    • Other preexisting health conditions.
    • Other lifestyle factors (exercise is probably the most important, but others may be involved as well).
    • Diet context. For example, we already know that the effect of eggs and dairy on heart health is influenced by diet context. [I have covered this for eggs in a previous issue of “Health Tips From the Professor”.]
    • Other unanticipated variables.

Only when we have identified variables that might influence the effect of calcium supplements on heart disease risk, will the scientific community be able to design studies to identify the population groups who might be adversely affected by calcium supplementation.

This would allow health professionals to make informed decisions about which of their patients should avoid calcium supplementation and which of their patients would benefit from calcium supplementation. 

2) We really don’t need the recommended RDAs for calcium to build strong bones. The Healthy Bonerecommended RDAs for calcium are 1,000 mg/day for adults 19-50, 1,000 mg/day for men and 1,200 mg/day for women 51-70, and 1,200 mg/day for both men and women over 70. But do we really need that amount of calcium to build healthy bones? 

I have discussed this topic in detail in a previous issue of “Health Tips From the Professor”. Here are the key points:

    • The current RDAs are based on calcium needs for people consuming the typical American diet and following the typical American lifestyle. If that is you, the current RDAs probably apply.
    • However, strong bones are absolutely dependent on three things, adequate calcium, adequate vitamin D, and adequate weight-bearing exercise. Most recent studies of calcium supplementation and bone density include adequate vitamin D, but almost none of them include exercise. Previous studies have been inadequate.
    • The best calcium supplements contain certain nutrients besides vitamin D that optimize bone formation. I have listed those nutrients in the article cited above.
    • Our ability to use calcium to build strong bones is dependent on diet (something I call a bone-healthy diet) and lifestyle (something I call a bone-healthy lifestyle).
    • For more information on each of these points, read the article I referenced above.

In short, I agree that the current calcium RDAs may be too high for individuals consuming a bone-healthy diet and following a bone-healthy lifestyle. But the current calcium RDAs are likely accurate for people consuming the typical American diet and following the typical American lifestyle.

    • While we do not have a calcium RDA for populations following a bone healthy diet lifestyle, some studies suggest that 700-800 mg of calcium/day may be sufficient for this group.

3) Calcium from supplements is absorbed faster and gives higher blood level spikes than calcium from foods. That could be a problem because high blood levels of calcium are associated with calcification of our arteries, which is associated with increased heart disease risk. 

This is a theoretical concern, because high blood calcium levels from supplementation are transitory, while it is continuous high blood calcium levels that are associated with calcification of our arteries.

However, it is a plausible concern because most supplement companies design their calcium supplements based on how quickly they get calcium into the bloodstream rather than how effectively the calcium is utilized for bone formation. Here are my recommendations:

    • Choose a calcium supplement that provides RDA levels of vitamin D plus other nutrients shown to support strong bone formation.
    • Choose a calcium supplement supported by clinical studies showing it is effectively utilized for bone formation.

4) We should be getting our calcium from foods rather than supplements. dairy foods

While it is always easy for doctors to recommend that we get our nutrients from food rather than supplements, they need to ask whether we are getting those nutrients from our diet. For calcium the data are particularly sobering.

    • The average American gets around 740 mg of calcium/day from their diet. That is probably enough for the small percentage of Americans following a bone healthy diet and lifestyle. But it is 260-460 mg short of the 1,000-1,200 mg/day recommended for older adults with the typical American diet and lifestyle.
      • And for the average American, around 70% of their calcium intake comes from dairy foods.


      • So, Americans who are following a typical American diet and lifestyle and are restricting dairy may require 800-1,000 mg/day of supplemental calcium unless they carefully plan their diets to optimize calcium intake.


      • Finally, vegans average about 550 mg/day from their diet. That might be borderline even if they were following a bone healthy lifestyle.
    • In short, we cannot assume our diet will provide enough calcium for strong bones unless we include dairy foods and/or plan our diet very carefully. Some degree of supplementation may be necessary.

How Much Calcium Do You Need?

Questioning Woman

I have covered a lot of territory in this article, so let me summarize the four concerns of the medical community and answer your most important question, “Should you take calcium supplements?”

1) Calcium supplements may increase the risk of heart disease for some people.

That is true, but we have no idea at present who is at increased risk and who isn’t. So, we should minimize our risk by taking the precautions I describe below.

2) We don’t need RDA levels of calcium to build strong bones. That is probably true if you are one of the few people who follows a bone healthy diet and lifestyle, but it isn’t true if you follow the typical American diet and lifestyle.

  • The current RDAs of 1,000 – 1,200 mg/day are a good guideline for how much calcium you need if you follow the typical American diet and lifestyle.
  • If you a one of the few people who follow a bone healthy diet and lifestyle (For what that involves, read this article) you may only need 700-800 mg/day. But we don’t have clinical studies that can tell us what the actual RDA for calcium should be under those circumstances.

3) Calcium from supplements is absorbed faster and gives higher blood calcium spikes than calcium from foods. You may remember that the theoretical concern is that even short-term spikes of high blood calcium may lead to calcification of your arteries, which increases your risk of heart disease. So, the important question becomes, “What can we do to minimize these spikes in blood calcium levels?”

  • We should avoid calcium supplements that brag about how quickly and efficiently the calcium is absorbed. That could lead to calcium spikes. Instead, we should look for calcium supplements that are backed by clinical studies showing they are efficiently utilized for bone formation.
  • We should look for calcium supplements that include RDA levels of vitamin D and other nutrients that optimize bone formation. You will find more information on that in the same article I referenced above.
  • Some experts recommend that calcium supplements be taken between meals. But it is probably better to take them with meals because foods will likely slow the rate at which calcium is absorbed and reduce calcium spikes in the blood.
  • We are told to limit calcium supplements to less than 500 mg at any one time because calcium absorption becomes inefficient at higher doses. It might be even better to limit calcium to 250 mg or less at a time to reduce calcium spikes in the blood.

4) We should get calcium from foods rather than supplements.

  • Many Americans do not get enough calcium from diet alone, especially if they avoid dairy foods. So, some degree of calcium supplementation may be necessary. I have given some guidelines depending on your diet and lifestyle above.
  • The amount of supplemental calcium needed is relatively small. I do not recommend exceeding the RDA unless directed to by your health professional.

The Bottom Line 

Some studies say that calcium supplements increase heart disease risk while others say they decrease heart disease risk. The headlines veer between “killer calcium” and “beneficial calcium”.

The trend appears to be moving in a positive direction. In recent years most of the studies have suggested that calcium supplements either decrease heart disease risk or have no effect on heart disease risk.

However, the medical profession has been slow to take note of this trend. Most medical societies and health professionals have focused on earlier studies and are still recommending that their patients get calcium from food rather than from supplements.

A recent meta-analysis of 12 double-blinded randomized clinical trials with 87,899 participants comparing the effect of a calcium supplement versus a placebo on heart disease outcomes has just been published. This study found no effect of calcium supplementation on:

  • Heart attack.
  • Stroke.
  • Heart failure.
  • Cardiovascular mortality.
  • All-cause mortality.

The authors of the study concluded, “Calcium supplementation was not associated with myocardial infraction [heart attack], stroke, heart failure, and cardiovascular/all-cause mortality.

For more details and advice on whether you should follow your doctor’s recommendations for calcium supplementation read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure or prevent any disease.

 _____________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

____________________________________________________________________

About The Author

Dr. Steve ChaneyDr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.


Is Vegan Breast Milk Sufficient?

What Can Vegan Moms Do?

Author: Dr. Stephen Chaney 

breastfeedingA whole food vegan diet is incredibly healthy:

  • Vegans are less likely to be overweight than the general population.
  • Vegans have a lower risk of diabetes, heart disease, cancer, hypertension, and several other diseases than the general population.
  • Whole food vegan diets are anti-inflammatory, so they lower the risk of autoimmune diseases and the “itis” diseases.

But vegan diets leave out meat, dairy, and eggs. Vegetarians without proper dietary advice are at high risk of inadequate intake of vitamin B12, vitamin D, iron, iodine, calcium, and DHA. And, of course, the risk of inadequate intake is even greater for vegans than it is for vegetarians, who may include some dairy and eggs in their diet.

So, it is legitimate to ask whether a vegetarian or vegan diet is sufficient for pregnancy and lactation. The short answer is that they can be if they are properly designed and properly supplemented.

But that is not an easy task, as evidenced by a recent study (N Ureta-Velasco et al., Nutrients 15:1855, 2023) comparing the breast milk of omnivore moms with the breast milk of vegetarian and vegan moms.

How Was This Study Done?

clinical studyThis study was done with 92 omnivore moms, 9 vegetarian moms (5-ovo-vegetarian and 4 lacto-ovo-vegetarians) and 11 vegan moms between August 2017 and February 2020 at the Regional Human Milk Bank at the “12 de Octubre” University Hospital in Madrid, Spain. The vegetarian and vegan moms were grouped together for data analysis.

On Day 0 of the study, participants went to the regional milk bank for blood and urine samples to determine nutritional status, a screening to determine health and socioeconomic status, and for food frequency questionnaire to characterize their habitual diet.

On days 1-5, they returned to the regional milk bank with a 24-hour diet recall of the previous day and to express 25 ml of breast milk to determine its nutrient content. On day 6, they returned to express a larger sample of breast milk to determine its lipid content (including EPA and DHA).

Note: Both the food frequency questionnaire and the 24-hour dietary recalls included nutrients derived from supplements.

What Did The Study Show About Dietary Intake of Key Nutrients?

Questioning WomanThis was a comprehensive study, so I will just cover the highlights here:

Birth Weight: Compared to the children of omnivore moms, the children of vegetarian/vegan moms were more likely to:

  • Have less weight gain during pregnancy (2 pounds less on average).
  • Be underweight at birth (60% of babies born to vegetarian/vegan moms were in the underweight category of birth weights versus 25% for babies born to omnivore moms).

This is probably because vegetarian/vegan moms:

  • Consumed slightly fewer calories per day (2146 versus 2319).
  • Consumed significantly less protein (67 g/d versus 96 g/d).
  • Were 10 times more likely to be underweight prior to pregnancy (10% versus 1%).

This is a concern because low birth weight increases the risk of physical and mental health issues later in life.

Supplement Use: The nutrients of greatest concern in a vegetarian/vegan diet are vitamin B12, vitamin D, iron, iodine, calcium, and DHA. For all these nutrients except DHA, this message appears to have gotten out to most vegetarian/vegan mothers because they were compensating for these potential deficiencies through supplementation.

For example, when they looked at average daily intake of these key nutrients from supplements, they found:

Nutrient Vegetarian/Vegan Moms Omnivore Moms
Vitamin D 1,080 IU (27mcg) 240 IU (6 mcg)
Folic acid 400 mcg 280 mcg
Vitamin B12 312 mcg 2 mcg
Calcium 566 mg 164 mg
Iron 40 mg 29 mg
DHA 100 mg 180 mg

However, that doesn’t tell the whole story, because not all vegetarian/vegan moms took supplements. When the investigators looked at the percent taking supplements, this is what they found.

Nutrient Vegetarian/Vegan Moms Omnivore Moms
Vitamin D 50% 50%
Folic acid 35% 61%
Vitamin B12 85% 60%
Calcium 15% 37%
Iron 25% 43%
DHA 10% 16%

Dietary Intake (Food + Supplements): The extra supplementation clearly played an important role because when the investigators looked at the overall intake from food and supplements, they found:

Nutrient Vegetarian/Vegan Moms Omnivore Moms
Vitamin D 224 IU (5.6 mcg) 432 IU (10.8 mcg)
Folate + Folic acid 668 mcg 473 mcg
Vitamin B12 258 mcg 6.9 mcg
Calcium 910 mg 1148 mg
Iron 31 mg 25 mg
DHA 110 mg 380 mg

Again, this doesn’t tell the whole story. Some women didn’t supplement. When the investigators looked at the percentage of women getting an inadequate intake of key nutrients from food plus supplements they found:

Nutrient Vegetarian/Vegan Moms Omnivore Moms
Vitamin D 75% 88%
Folate + Folic acid 0% 39%
Vitamin B12 25% 0%
Calcium 45% 40%
Iron Not reported Not reported
DHA Not reported Not reported

These results clearly show the need for supplementation. While the average intake from food plus supplements looked good, there were a significant percentage of women who weren’t getting adequate intake of key nutrients because they didn’t supplement.

The exceptions were folate + folic acid for vegetarian/vegans because their diet is rich in folate-containing foods and vitamin B12 for omnivores because their diet is rich in foods containing B12.

Is Vegan Breast Milk Sufficient?

Of course, the proof is in the pudding. When the investigators looked at the nutrient content of breast milk, this is what they found:

Nutrient Vegetarian/Vegan

Moms

Omnivore

Moms

Reference

Value*

Vitamin D3 1.1 mcg/L 3.4 mcg/L 0.25-2 mcg/L
Folate + Folic acid 19 mcg/L 20 mcg/l 80 mcg/L
Vitamin B12 0.74 mcg/L 0.65 mcg/L 0.5 mcg/L
Calcium 83 mg/L 99 mg/L 200-300 mg/L
Iron Not reported Not reported
DHA 0.15 g/100 g fat 0.33 g/100 g fat 0.35 g/100 g fat

*Reference values established by WHO

  • The chief difference between breast milk from vegetarian/vegan moms was in DHA levels.
  • That’s because the diet of vegetarians and vegans contains very little DHA, and very few vegetarian/vegan women in this study supplemented with DHA.
  • This study also found that breast milk from both vegetarian/vegan moms and omnivore moms was low in folate + folic acid, calcium, nicotinamide, and selenium. They said that requires follow-up in future studies.

The authors concluded, “The most important contribution of this study is the detailed and comprehensive description of micronutrients and lipids in human milk from omnivore milk donors and vegetarian/vegan women…Of particular concern is the lower DHA content in the milk of our vegetarian/vegan group. However, raising awareness and administering proper supplementation could bridge the gap, as has been the case with vitamin B12.”

What Can Vegan Moms Do?

This study emphasizes the importance of careful planning and supplementation during pregnancy and lactation if you are a vegetarian or vegan mom.

For example, the vegetarian/vegan women in this study were more likely to have low birthweight babies, and low birthweight infants are at risk for health issues later in life. That means:

  • Careful planning is required to select calorie- and protein-rich plant foods.
  • A high-quality plant protein supplement can be a great help.

Supplementation is particularly important during lactation to assure your breast milk adequately nourishes your newborn baby. For example, in this study:

  • The vitamin B12 level in the breast milk from vegetarian/vegan moms was adequate because 85% of them supplemented with vitamin B12.
  • The DHA level in the breast milk from vegetarian/vegan moms was inadequate because only 10% of them supplemented with DHA.
  • The authors of this study recommended that vegetarian and vegan moms consume at least 200 mg of DHA from algal sources while they are breastfeeding.

However, finding a prenatal supplement that provides all the nutrients you need prior to pregnancy, during pregnancy, and while breastfeeding is challenging. I gave you 7 tips for choosing the best prenatal supplements in a previous “Health Tips From the Professor” article.

The Bottom Line 

A recent study asked whether the breast milk of vegetarian and vegan moms was sufficient for the needs of their newborn babies. The study found that:

  • Folate levels in their breast milk were sufficient because the diets of vegetarians and vegans contain many folate-rich foods.
  • Vitamin B12 levels in their breast milk were sufficient because 85% of the vegetarian and vegan women in this study supplemented with vitamin B12.
  • DHA levels in their breast milk were insufficient because the diets of vegetarian and vegan women are very low in DHA, and only 10% of the women in this study supplemented with DHA.
  • The authors of this study recommended that vegetarian and vegan moms consume at least 200 mg of DHA from algal sources while they are breastfeeding.

This study reinforces the need for supplementation during lactation to assure your breast milk adequately nourishes your newborn baby.

However, finding a prenatal supplement that provides all the nutrients you need prior to pregnancy, during pregnancy, and while breastfeeding is challenging. I gave you 7 tips for choosing the best prenatal supplement in a previous “Health Tips From the Professor” article.

For more information on this study read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

___________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance


Prenatal Supplements Strike Out Again

Is It Three Strikes And You Are Out?

Author: Dr. Stephen Chaney

Pregnant CoupleIf you are pregnant, you want the best for your unborn baby. Your doctor has recommended a prenatal supplement, but do the prenatal supplements on the market meet your needs? A few months ago, I shared two studies that concluded that most prenatal supplements on the market are woefully inadequate.

In fact, the authors said, “[Our] analysis found that prenatal supplements vary widely in content, often only contain a subset of essential vitamins, and the levels were often below…recommendations.”

In other words, their study found that most prenatal vitamins on the market may not be adequate to support your needs and the needs of your child through pregnancy and breastfeeding.

Now, a third study on the topic has been published (KA Saunders et al, American Journal of Clinical Nutrition, 117: 823-829, 2023. It differs from the previous studies in that:

1) The previous two studies took a comprehensive approach, while this study focused on 6 key nutrients.

  • The previous studies included all nutrients important for a healthy pregnancy including choline, iodine, and vitamin K, which have only recently been shown to be important for a healthy pregnancy.
  • This study focused on 6 nutrients, vitamin A, vitamin D, folic acid, calcium, iron, and omega-3 fatty acids, which have long been recognized as essential for a healthy pregnancy.

2) The previous two studies focused on prenatal supplements, while this study focused on all supplements that might be taken by pregnant women.

3) The previous two studies asked whether supplements provided recommended amounts of all nutrients needed for a healthy pregnancy. This study took a “Goldilocks approach” and asked whether levels of these 6 essential nutrients were appropriate (“just right”). The study:

  • Started by determining the intake of these 6 key nutrients by American women. The authors of the study then added the amount of each nutrient provided by the supplements in their study to the amount of that nutrient in the diet of American women and:
    • Calculated the minimum amount of each nutrient that would be needed to assure that 90% of American women taking a particular supplement would meet the recommended intake for pregnant and lactating women.
    • Calculated the maximum amount of each nutrient provided by supplements in their study to assure that that 90% of American women taking that supplement would not get potentially toxic amounts of that nutrient.
  • In other words, for each of the 6 nutrients they calculated a supplemental dose range that was neither too low nor too high. They called this the “appropriate dose range” for each nutrient. Goldilocks would have called it “just right”.

I’m sure you are anxiously waiting to learn what their study found. But before we go there, I will describe how the study was done.

How Was The Study Done?

clinical studyFor the dietary intake portion of the study, the authors used dietary intake data previously collected from the Environmental Influences on Child Health Outcomes (ECHO) study.

The ECHO study is a consortium of 69 medical centers across multiple states. It is an observational study of mothers and their offspring designed to understand the effects of early life exposures on child health and development.

The current study analyzed dietary intake data for 2450 participants from 6 medical centers across 5 states in the ECHO study. The women in this study were diverse with respect to ethnicity, education, and weight.

All pregnant women in the current study completed at least one 24-hour dietary recall between 6-week gestation until delivery (24% completed one dietary recall. 76% completed two or more dietary recalls). Dietary intake was generally assessed with an expert interviewer and included all foods and beverages consumed in the previous 24 hours.

For the supplement portion of the study, the authors used the NIH Dietary Supplement Label Database because it is the most complete listing of supplements in the US. The authors selected 20,547 supplements that contained at least one of the 6 essential nutrients from this database.

To determine which of the 20,547 supplements contained appropriate levels of the 6 nutrients (vitamin A, vitamin D, folic acid, calcium, iron, and omega-3 fatty acids) selected for this study, the authors used the process described in the introduction above. Briefly:

  • The authors added the amount of each nutrient provided by the supplements in their study to the amount of that nutrient in the diet of American women and:
  • Calculated the minimum amount of each nutrient that would be needed to assure that 90% of American women taking a particular supplement would meet the recommended intake for pregnant and lactating women.
  • Calculated the maximum amount of each nutrient provided by supplements in their study to assure that that 90% of American women taking that supplement would not get potentially toxic amounts of that nutrient.

In other words, for each of the 6 nutrients they calculated a supplemental dose range that was neither too low nor too high. They called this the “appropriate dose range” for each nutrient.

Why Are The 6 Nutrients Included In This Study Important?

Dietary Intake Is Often Inadequate

The diet analysis of pregnant American women in this study found:

  • 42% were at risk of inadequate vitamin A intake.
  • 96% were at risk of inadequate vitamin D intake.
  • 45% were at risk of inadequate folic acid intake.
  • 55% were at risk of inadequate calcium intake.
  • 93% were at risk of inadequate iron intake.
  • 67% were at risk of inadequate omega-3 intake.

The percentage of women at risk for inadequate intake of these nutrients varied with age, ethnicity, and income levels. But the overall message is clear. Most American women are not getting enough of these essential nutrients from their diet alone.

The Risk of Inadequate and Excessive Intake Of These Nutrients

These 6 nutrients were chosen in part because reviews by the Cochrane Collaboration have concluded that inadequate intake of these nutrients are associated with complications during pregnancy and delivery. They can also adversely affect the health and normal development of the baby.

This is important because the Cochrane Collaboration is considered the Gold Standard of clinical studies. You can find a more detailed description of Cochrane Collaboration studies and why they are the Gold standard here.

[Note: The Cochrane Collaboration has not yet evaluated choline, iodine, and vitamin K for pregnant women, but their inclusion in prenatal supplements is supported by multiple clinical studies.]

In addition, excess intake of all these nutrients except omega-3s can harm both the fetus and the mother. The is why the Food and Nutrition Board has set ULs (Upper Limits – the level above which toxicity can occur) for 5 of the 6 nutrients. This is important because previous studies have suggested that up to 25% of women may be getting toxic levels of one or more of these nutrients when you consider both their dietary intake and their prenatal supplement.

Summary

In other words, both too little and too much of these nutrients can harm the mom and her baby. It is critical that prenatal supplements get the dosing right.

It is for that reason that the authors of this study have set an “appropriate dose range” (high enough that 90% of women have enough of each nutrient to prevent deficiency and low enough that 90% of women do not exceed the UL for each nutrient) as the standard for evaluating the adequacy and safety of supplements for pregnant women.

Prenatal Supplements Strike Out Again

Of the 20,547 supplements (421 labeled as prenatal supplements) available on the US market as of December 31, 2022, the investigators reported that:

  • Only 69 (0.3%) supplements contained all 6 nutrients considered essential for a healthy pregnancy.
  • Only 1 supplement contained all 6 nutrients at the appropriate doses, and it wasn’t even labeled as a prenatal supplement.

In addition:

  • One supplement containing all 6 nutrients put 100% of the women in their study at risk for excessive intake of folic acid.
  • Another supplement containing all 6 nutrients put 46% of the women in their study at risk of inadequate calcium intake.

The authors concluded, “Almost no US dietary supplements provide key nutrients in the doses needed for pregnant women. Affordable and convenient products that fill the gap between food-based intake and estimated requirements of pregnancy without inducing excess intake are needed to support pregnant women and their offspring.”

In short, the conclusion of this study can be summed up as, “Prenatal Supplements Strike Out Again”.

[Note: It sometime takes a while for supplement labels to be posted in the NIH Dietary Supplement Label Database. The authors acknowledged that this study may not include supplements introduced or reformulated in the last quarter of 2022.]

Is It Three Strikes And You Are Out? 

pregnant women taking vitaminsIf you are pregnant or thinking of becoming pregnant, this should be a wake-up call.

70% of pregnant women in this country take prenatal supplements, usually based on recommendations by their health care provider. They assume the prenatal supplements meet their needs and the needs of their unborn baby.

Yet three studies evaluating the adequacy of prenatal supplements have been published in the past few months. They took very different approaches in evaluating the supplements. But all three studies concluded that the vast majority of prenatal supplements on the market are woefully inadequate.

You may be wondering, “Is it three strikes, and you are out?” Are there no decent prenatal supplements on the market?  The answer to those questions is, “No. There are good prenatal supplements on the market.”

You may be wondering how I can say that in the face of such overwhelming negative data. That’s because while all 3 studies were very good studies, they each had “blind spots”:

1) Each of the studies used very stringent criteria for identifying adequate prenatal supplements. In some cases, their criteria were stricter than the RDA recommendations and the recommendations of the American College of Obstetrics and Gynecology for pregnant and lactating women. It could be argued that their criteria were too stringent.

2) In the case of the current study, it could also be argued that evaluating only 6 nutrients is not a good criterion for evaluating the adequacy of prenatal supplements. For example, I looked up the one supplement rated as adequate in this study. It does provide appropriate doses of the 6 nutrients this study focused on. It also provides appropriate doses of vitamin K and iodine. But it does not provide choline. It is a very good supplement for women, but it is not the perfect prenatal supplement.

So, what can you do? How can you find the best prenatal supplement for you? Unfortunately, you cannot rely on advice from your friends or your health professional. You cannot rely on advertisements. That is a good place to start, but you have to do your own sleuthing.

With that in mind, I have listed 7 simple rules for selecting the best possible prenatal supplement in  my article about the first two studies. Use these rules for evaluating every prenatal supplement you come across. Happy sleuthing.

The Bottom Line 

A recent study evaluated all 20,547 supplements on the US market to see if they met the needs of pregnant women in this country.

  • They focused on 6 nutrients (vitamin A, vitamin D, folic acid, calcium, iron, and omega-3s) known to be essential for a healthy pregnancy.
  • They determined the dietary intake for all 6 nutrients in a cross section of pregnant women in the US.
  • They added the amount of the 6 nutrients in each of the 20,547 supplements to the dietary intake of those nutrients by pregnant women.
  • They then asked which supplements provided the “appropriate dose” of all 6 nutrients. They defined “appropriate dose” as the dose range that was.
    • High enough to prevent deficiency of that nutrient in 90% of pregnant women taking the supplement…and…
    • Low enough to prevent toxicity from that nutrient in 90% of pregnant women taking the supplement.
  • In other words, for each of the 6 nutrients they calculated a supplemental dose range that was neither too low nor too high.

Of the 20,547 supplements (421 labeled as prenatal supplements) available on the US market:

  • Only 69 (0.3%) supplements contained all 6 nutrients they considered essential for a healthy pregnancy.
  • Only 1 supplement contained all 6 nutrients at the appropriate doses, and it wasn’t even labeled as a prenatal supplement.

The authors concluded, “Almost no US dietary supplements provide key nutrients in the doses needed for pregnant women. Affordable and convenient products that fill the gap between food-based intake and estimated requirements of pregnancy without inducing excess intake are needed to support pregnant women and their offspring.”

[Note: It sometime takes a while for supplement labels to be posted in the NIH Dietary Supplement Label Database. The authors acknowledged that this study may not include supplements introduced or reformulated in the last quarter of 2022 or early 2023.]

If you are pregnant or thinking of becoming pregnant, this should be a wake-up call.

70% of pregnant women in this country take prenatal supplements, usually based on recommendations by their health care provider. They assume the prenatal supplements meet their needs and the needs of their unborn baby.

Yet three studies evaluating the adequacy of prenatal supplements have been published in the past few months. And all three studies concluded that the vast majority of prenatal supplements on the market are woefully inadequate.

You may be wondering, “Is it three strikes, and you are out?” Are there no decent prenatal supplements on the market?  The answer to those questions is, “No. There are good prenatal supplements on the market.”

You may be wondering how I can say that in the face of such overwhelming negative data. That’s because while all 3 studies were very good studies, they each had “blind spots”:

For more details on this study and 7 tips on finding the best prenatal supplement for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease. 

____________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance


Is Your Prenatal Supplement Adequate?

What Should You Look For In A Prenatal Supplement?

Author: Dr. Stephen Chaney

pregnant women taking omega-3You want to do the best for your unborn child. So, you try to find the best prenatal supplement. You may ask your doctor to recommend a prenatal supplement. You may ask your best friend what supplement she used when she was pregnant. Or perhaps you scan online reviews of prenatal supplements by random dietitians or nutrition gurus to select the “best” prenatal supplements.

Then you read the supplement label or the company’s website and see claims like:

  • “Supports optimal nutrition before, during, and after pregnancy”
  • “Packed with 16 nutrients to support fetal development, immunity, energy metabolism, and more”
  • “Concise prenatal formula supports both bone and brain development”

It sounds so good. You think you have found the perfect prenatal supplement. “Right?”

Perhaps not. A recent study (JB Adams et al, Maternal Health, Neonatology, and Perinatology, 8:4, 2022) did an in-depth review of prenatal supplement recommendations and how well prenatal supplements on the market met those recommendations.

The results were not encouraging. The authors concluded, “[Our] analysis found that prenatal supplements vary widely in content, often only contain a subset of essential vitamins, and the levels were often below…recommendations.”

In other words, their study found that most prenatal vitamins may not be adequate to support your needs and the needs of your child through pregnancy and breastfeeding.

I know this is likely to be a topic of great concern for many of you. So, I will examine the study in detail and give you some guidelines for selecting the perfect prenatal supplement.

How Was This Study Done?

clinical studyThis study can be divided into two parts.

#1: What Should The Ideal Prenatal Supplement Contain:

The authors started off by reevaluating the optimal recommendations for prenatal supplements. They reviewed over 200 articles, focusing on articles that:

  • Provided insight into optimal dosage [of essential nutrients] such as treatment studies on the effects of different doses on outcomes and biomarkers.
  • Were larger, more rigorously designed, such as randomized double-blind placebo-controlled studies.

The studies included in their review fell into three categories:

  1. The association of low levels of vitamins with health problems [during pregnancy and in the child after birth].

2) Studies on the changes in [blood] vitamin levels during pregnancy [when the mother is either] un-supplemented or supplemented (The blood level of many vitamins decreases dramatically during pregnancy without supplementation).

3) Clinical trials on the effect of vitamin supplementation on health problems [during pregnancy].

They used these data to create their recommendations for what an ideal prenatal supplement should contain. In some cases, their recommendations were higher than current RDA recommendations for pregnant women.

#2: How Do Currently Available Prenatal Supplements Compare With Their Recommendations For The Ideal Supplement?

For this part of the study, they created a comprehensive list of the nutrients provided by 188 prenatal supplements currently on the market using databases created by the National Institutes of Health. Where these databases were outdated, the nutrient list for that supplement was updated using information on the manufacturer’s websites or labels on retail websites such as Amazon.

Finally, they compared the nutrient content of all 188 prenatal supplements with their recommendations for the ideal prenatal supplement.

Is Your Prenatal Supplement Adequate?

Questioning WomanThere are four points I wish to make before I review the results of this study.

  1. I suspect you are most interested in finding out how prenatal supplements on the market compare with their recommendations for an ideal supplement, so that is what I will discuss below.

2) As I mentioned above, some of their recommendations exceed the current Daily Value (DV) recommendations for pregnant and lactating women. I will point that out whenever it significantly affects the comparisons.

3) The authors of this article made the point that most women going on a prenatal supplement will probably discontinue taking their multivitamin supplement. Thus, their recommendations included nutrients commonly included in multivitamin supplements. This is a valid point, and something you should consider when choosing a prenatal supplement. However, in my discussion below I will focus on the nutrients that are universally recognized as important for pregnancy and lactation.

4) The authors focused on prenatal supplements that had less than the recommended amount of essential nutrients. They did not ask how many of those supplements had excessive amounts of certain nutrients. In my non-systematic review of prenatal supplements, I found several that had doses of some nutrients in thousands of percent of the DV recommendations. In my opinion, this is potentially unsafe for pregnancy and nursing. I will cover this topic in more detail in my discussion.

With that in mind, here are the results of their review.

Vitamins:

When you look at vitamins that have long been recognized as essential for pregnant women, the results are encouraging:

  • Vitamin D, folate, vitamin B12, and vitamin B6 are found in adequate amounts compared to the DV in most prenatal supplements.

However, when you look at nutrients that have more recently been recognized as essential for pregnant women, the story is very different:

  • For vitamin K only 31% of prenatal supplements contain vitamin K and only 16% meet or exceed their recommendation for vitamin K.
    • Their recommendation (90 mcg/day) is identical to the DV for vitamin K. So, there is no doubt that most prenatal supplements do not provide adequate amounts of vitamin K.
  • For choline only 40 % of prenatal supplements contain choline and only 2% meet or exceed their recommendation for choline.
    • Their recommendation (350 mg/day) for choline is less than the 450 mg/day recommended by the NIH and the American College of Obstetricians and Gynecologists.
    • The average prenatal supplement only provides 25 mg of choline, which is wildly inadequate by any standard.
  • For DHA only 42% of prenatal supplements contain DHA and only 1% meet or exceed their recommendation for DHA.
    • Their recommendation (600 mg/day) for DHA is higher than the 200 – 300 mg/day recommended by the most health organizations.
    • However, the average prenatal supplement only provides 94 mg of DHA, so even at 200 – 300 mg/day a substantial percentage of prenatal supplements do not provide adequate amounts of DHA.

Minerals:

calcium supplementsThis study did not consider minerals, so I will draw on another source to estimate the adequacy of minerals in prenatal supplements.

Three key minerals for a healthy pregnancy are iron, calcium, and iodine (Yes, I realize that iodine is not a mineral, but it is usually listed with the minerals on supplement labels. And it is also essential for a healthy pregnancy). Fortunately, another recent study (LG Saldanha et al, Journal of the American Academy of Dietetics, 117: 1429-1436, 2017) looked at the adequacy of these nutrients in 214 prenatal supplements. This study found:

  • The iron DV for pregnant and lactating women is 27 mg/day and 95% of prenatal supplements contained iron at the recommended level.
  • The calcium DV for pregnant and lactating women is 1,300 mg/day. A high percentage (91%) of prenatal supplements contain calcium, but many prenatal supplements only provide 100-200 mg of calcium. That is far less than the DV.
  • The situation for iodine is even more alarming. Only 50% of prenatal supplements contain iodine. And for those that do contain iodine, the average iodine content is only 150 mcg (The DV for pregnant and lactating women is 290 mcg/day).

It is no wonder the authors of these two studies concluded that most prenatal supplements on the market do not provide adequate amounts of all the nutrients needed for a healthy pregnancy. The shortfalls are particularly acute for vitamin K, choline, DHA, iodine, and calcium.

What Should You Look For In A Prenatal Supplement?

Questioning WomanBy now you are probably wondering how you know a good prenatal supplement from a bad one. Here are six simple rules for choosing the ideal prenatal supplement.

  1. Don’t rely on health “gurus” to choose your prenatal supplement for you. I did a little “sleuthing” for you. I searched the internet for websites claiming to have identified the “best” prenatal supplements. I checked out the supplements they recommended, and here is what I found:
  • The supplements the gurus recommended checked all the boxes in that they had some of all the nutrients required for a healthy pregnancy.
  • However, the amount of those nutrients ranged from lows of 10-20% of the DV for pregnant and lactating women to thousands of percent of the DV for others.
  • In other words, they contained grossly inadequate levels of some nutrients and potentially toxic levels of others.

2) Don’t believe label claims or claims made on the manufacturer’s website. Remember the claim, “Concise prenatal formula supports both bone and brain development”, that I mentioned at the beginning of this article? The supplement associated with that claim had only 100 mg of calcium and no DHA. It is hard to imagine a supplement like that supporting either bone or brain health. The claim was bogus.

3) Don’t assume your doctor’s recommendation is the ideal prenatal supplement. A recent study (LG Saldanha et al, Journal of the American Academy of Dietetics, 117: 1429-1436, 2017) compared prescription (the kind your doctor is likely to prescribe) and non-prescription prenatal supplements. It found:

  • Compared with non-prescription supplements, prescription supplements contained significantly fewer vitamins (9 versus 11) and minerals (4 versus 8).
  • While prescription supplements contained more folic acid than non-prescription supplements, they contained significantly less vitamin A, vitamin D, iodine, and calcium.

4) Look for a prenatal supplement containing all the essential nutrients, not just those important for a healthy pregnancy. The authors of the first study made the point that most women will stop taking their regular multivitamin when they start their prenatal supplement. If that is you, your prenatal supplement should contain the nutrients you were getting from your multivitamin.

5) Look for a prenatal supplement that provide 100% of DV for all nutrients except the bulky ones. The ideal prenatal supplement should contain 100% of the DV for pregnant and lactating women for all essential nutrients. Avoid supplements with very low amounts of some nutrients and large excesses of others.

  • Bulky nutrients like calcium, magnesium, and choline are exceptions. It would be hard to get 100% DV for those nutrients in any supplement you could swallow.

6) Look for a prenatal supplement that “fills the gap” for bulky nutrients.

  • Fortunately, the NIH has estimated how much of these nutrients the average American woman gets in her diet. That allows us to estimate how much the average woman needs to get from her prenatal supplement to bring her total intake up to the DV for pregnant and lactating women. That amounts to 458 mg for calcium, 166 mg for magnesium, and 272 mg for choline.
    • That gives you a reasonable benchmark for assessing whether a prenatal supplement is providing enough of those important nutrients. When you read their labels, you will find most prenatal supplements are woefully inadequate for these nutrients.
    • You also need to ask whether your diet is “average”. For example, the average American gets 72% of their calcium from dairy foods. If you do not consume dairy, you may need to get more calcium from your supplement.

7) Avoid the excesses. Your unborn baby is precious. You don’t want to expose it to potentially toxic doses of vitamins or minerals. Avoid any prenatal supplement containing thousands of percent of the DV for some nutrients. And I would recommend caution with supplements containing over 200% of the DV for some nutrients if you are taking other supplements that may provide the same nutrient(s).

The Bottom Line 

Two recent studies have surveyed hundreds of prenatal vitamins and asked whether they provided adequate amounts of the nutrients that are essential for a healthy pregnancy. The results were shocking.

  • While most prenatal supplements provided adequate amounts of folic acid, vitamin B12, vitamin B6, vitamin D, and iron…
  • They were woefully inadequate for vitamin K, calcium, choline, iodine, and DHA – all nutrients that are essential for a healthy pregnancy.
  • Furthermore, prescription prenatal supplements (the kind your doctor is likely to prescribe) were no better than non-prescription supplements.

The authors of the first study concluded, “[Our] analysis found that prenatal supplements vary widely in content, often only contain a subset of essential vitamins, and the levels were often below…recommendations.”

In other words, their study found that most prenatal vitamins on the market may not be adequate to support your needs and the needs of your child through pregnancy and breastfeeding.

For more details on this study and my discussion of how you can select the ideal prenatal supplement for you and your unborn child, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease


Health Tips From The Professor